When Sleep Turns Dangerous

Raina Heverin, 44, was left with a brain injury after plunging 40 feet from a balcony while sleepwalking on holiday in Paris. She suffered a bleed on the brain, a punctured lung, and a broken hip, arm and ribs, and spent three weeks in a coma.

Woman sleepwalking in bedroom at night while man sleeps on bed

This August 2026 Parisian case, and multiple reports filed on the National Library of Medicine since at least 2012, underscores how devastating sleepwalking can be. Sometimes called Elpenor syndrome, such falls are the primary way sleepwalking causes brain injury. Impaired perception during sleepwalking episodes can, for example, lead to falls from staircases and balconies. A meta-analysis of 51 studies found the estimated lifetime prevalence of sleepwalking was 6.9%, with current adult prevalence around 1.5%. (Though this meta-analysis was published, and made available on the NLM database, in November 2016, the findings remain notable.)

Traumatic brain injury can also precipitate devastating sleep disorders. Sleep disturbances overall affect 30% – 70% of persons after traumatic brain injury, in the forms of insomnia, fatigue, narcolepsy (with or without cataplexy, the sudden, brief loss of voluntary muscle control or tone), sleep apnea (obstructive and/or central), periodic limb movement disorder, and parasomnias. [In rehabilitation centers, parasomnias were the presenting complaint in 25% of patients with brain trauma.]

For prevention, doctors recommend brain injured patients create a safe sleep environment: remove sharp objects, lock doors and windows, install safety gates on staircases, and use door alarms. Maintaining a consistent sleep schedule that includes an hour before bed to mentally decompress is also important. Those with brain injury may want to consult with a sleep specialist, since these parasomnias frequently go underrecognized.

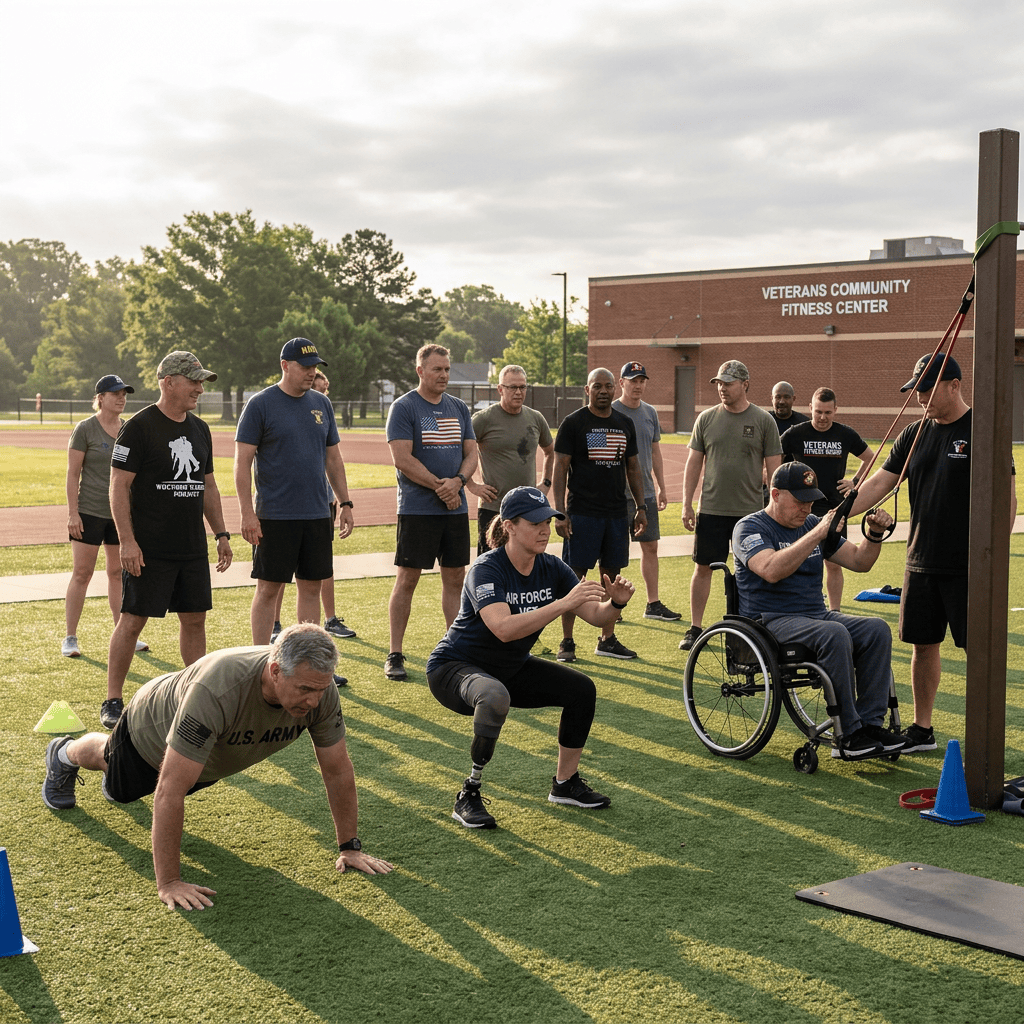
Morning Joe’s Benefits Come with Caution for TBI Survivors

brain made of coffee swirling

The day doesn’t truly begin until that first cup of coffee is in hand for a countless number of people. It’s ritual, comfort, and fuel! However, what does caffeine do to an injured brain?

According to a June 2025 article from Nutrients, a peer-reviewed journal that is also available on PubMed, research revealed that caffeine can function both as a neuroprotectant and a neurotoxin for those with a traumatic brain injury. Whether it can be a boon or a burden hinges on dosage, timing, and context. At low-to-moderate amounts, such as a morning brew, caffeine may reduce TBI-associated inflammation, oxidative stress, and intracranial pressure, enhance alertness and reduce mental fatigue, critical for cognitive rehabilitation. On the other hand, in young people experiencing repetitive moderate TBI, it was found that caffeine consumption disrupts normal brain pruning processes. This can potentially lead to further neurological and behavioral impairments.

Adding to this complex connection, Neuropharmacology, a journal that focuses on research about neuroscience that can also be found on PubMed, published the findings of a 2026 University College London study about caffeine citrate, a medication used to treat a lack of breathing in premature babies: while intended to stimulate breathing centers, higher doses of caffeine citrate can result in toxicity. (However, it appears that the “babies” that were studied were piglets.)

The takeaway is similar to that of other treatment possibilities: your coffee habit may be doing your brain favors – or not – so caution is warranted.

Benefits of Exercise after TBI

Veterans performing adaptive fitness exercises on an outdoor athletic field

In 2013, the University of Buffalo found that of the four participants who underwent daily aerobic exercise, all benefited neurologically, particularly in decreasing exhaustion.  In 2015, the National Institute of Health (NIH) conducted a 12-week study with the same results: “individuals with TBI may benefit from participation in vigorous aerobic exercise training with improved cardiorespiratory fitness and diminished fatigue.”  Currently, the University of Kansas is performing a two-year, $500,000 clinical study, sponsored by the Department of Defense, to see if the same applies to wounded warriors.  (The reason why this is even a question is because traditionally, rest is the recommended remedy for a “knock to the head”.)

As opposed to the Buffalo study, the study in Kansas will include more than 100 hundred wounded warriors, stationed in Fort Riley, all of whom were affected by explosive devices.  Also, as the leaders of the study and exercise trainers will agree, all exercise is not the same and does not provide to same benefits.  Therefore, “instead of lifting weights, we want the soldiers running more to improve their aerobic capacity,” says David Johnson, the leader of the study, explaining the aim of the study in a news release.  Beyond fatigue, the study expects to find that aerobic exercise helps the brain heal in other ways, such as in memory and thinking, anxiety and depression.  While this study is focused on the benefits of exercise for those with mild traumatic brain injury, the results may have benefits for other neurological conditions, such as in aiding those with severe TBI, Alzheimer’s disease, etc.  More so, it could reaffirm the neurological benefits of exercise for all.